Hong Kong health officials recently flagged twenty-one mpox cases since August, wheeling out the standard, predictable machinery of bureaucratic alarmism. The prescription is always identical. High-risk groups must roll up their sleeves for jabs, stay vigilant, and treat every minor skin anomaly as a harbinger of doom.
It is a lazy diagnosis wrapped in institutional anxiety. Don't forget to check out our earlier article on this related article.
For years, the public health apparatus has treated every viral blip as an existential crisis, relying on a blunt-force toolkit designed for a different era. Mpox is not smallpox, and treating it with the same panic playbook does more damage to public trust than the virus ever will. When authorities scream emergency at every statistical ripple, people tune out. That is not public health. That is crying wolf.
Let us look at the actual mechanics of what is happening here. If you want more about the history here, WebMD provides an informative summary.
The Flawed Premise Of Mass Vaccination As A Blanket Shield
The core narrative pushed by health bureaus is straightforward: see a cluster, push the jab, declare victory. But this ignores the granular epidemiological reality of transmission vectors. Mpox is overwhelmingly driven by specific, highly localized social networks. Spraying vaccine messaging across broad demographics while ignoring the actual behavioral dynamics of transmission is lazy policymaking.
I have watched public health budgets burn through millions of dollars on broad awareness campaigns that achieve identical baseline results to targeted, peer-led interventions that cost a fraction of the price. Institutions love mass campaigns because they look proactive on paper. They allow bureaucrats to issue press releases claiming they did something.
What they actually achieve is misallocation of resources.
When you tell everyone to worry equally, you ensure that nobody knows how to protect themselves effectively. Real risk mitigation requires radical honesty about who is actually vulnerable and how transmission occurs. Instead, we get sanitized bureaucrat-speak designed to avoid offending sensibilities while failing to inform the people who actually need actionable data.
Why The Symptoms Of Institutional Panic Are Worse Than The Disease
The panic response introduces a secondary contagion: behavioral distortion. When a handful of cases triggers a media blitz, hospitals see surges of terrified people showing up with unrelated rashes, mosquito bites, and benign dermatological conditions. Resources that should be directed toward chronic care and true emergencies get sucked into the black hole of viral anxiety.
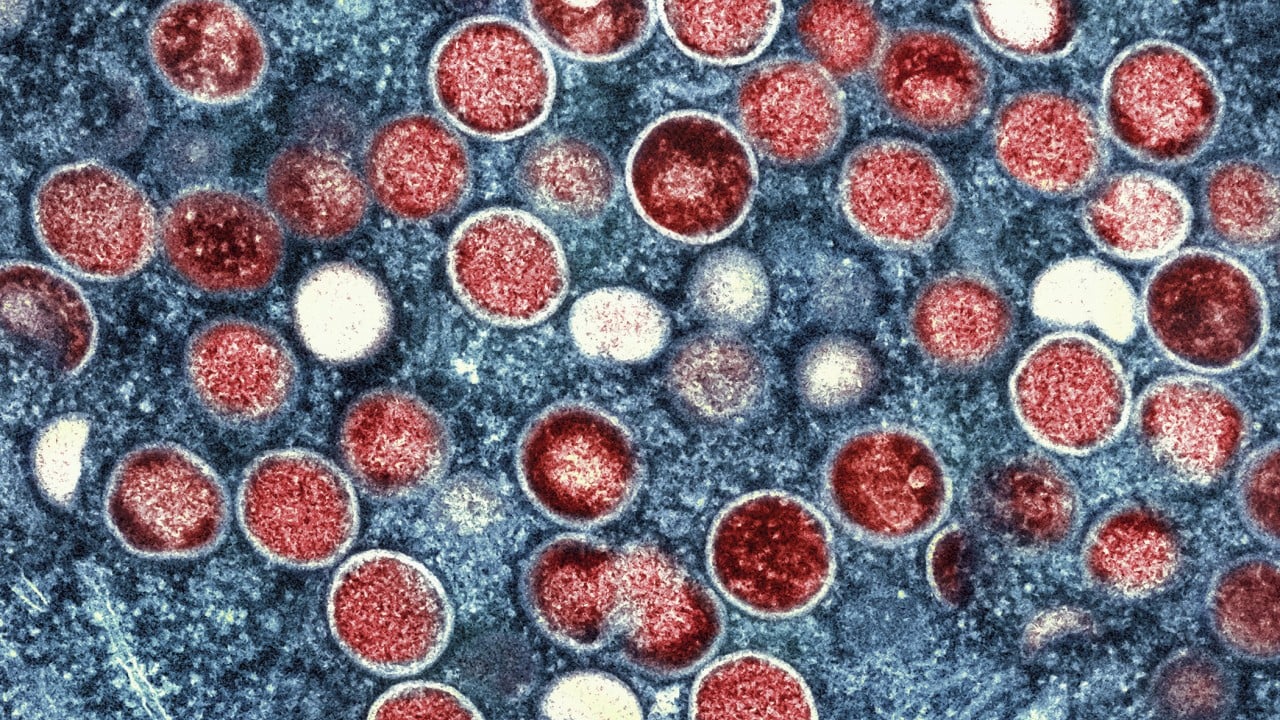
Let us be precise about what mpox actually is in this context. It is a self-limiting orthopoxvirus. For the vast majority of individuals who contract it, the clinical course is unpleasant, painful, and entirely manageable with supportive care. Yet the framing implies an unstoppable plague requiring draconian behavioral shifts.
This disconnect between clinical reality and institutional rhetoric creates a credibility deficit. When people realize the sky is not falling, they stop believing health authorities when real crises hit. You cannot cry emergency over every localized cluster without paying a heavy tax on public trust down the road.
The Uncomfortable Truth About Risk Management
Here is the part the official press releases leave out. Risk is not distributed evenly across a population, and pretending it is does not make society safer. It just makes policy ineffective.
If you are serious about driving down case numbers in Hong Kong or anywhere else, you stop relying on generic public service announcements that get buried in social media feeds. You go straight to the communities affected. You work with trusted local organizations, sexual health clinics, and grassroots networks. You provide accurate, non-judgmental information about incubation periods, lesion presentation, and early isolation protocols.
That requires cultural competence and institutional humility. Two things that are notoriously scarce inside government health departments.
The twenty-one cases recorded since August are a blip, not a wave. They represent baseline viral circulation in an interconnected global hub. Treating them like the opening act of an apocalypse is an insult to the intelligence of the public.
Stop treating adults like children who need to be frightened into compliance. Give people the unvarnished facts, back off the theatrical panic, and let targeted interventions do the work they were designed to do.
The next time an official tells you to panic over a double-digit case count, ask yourself who benefits from the fear. It certainly is not you.