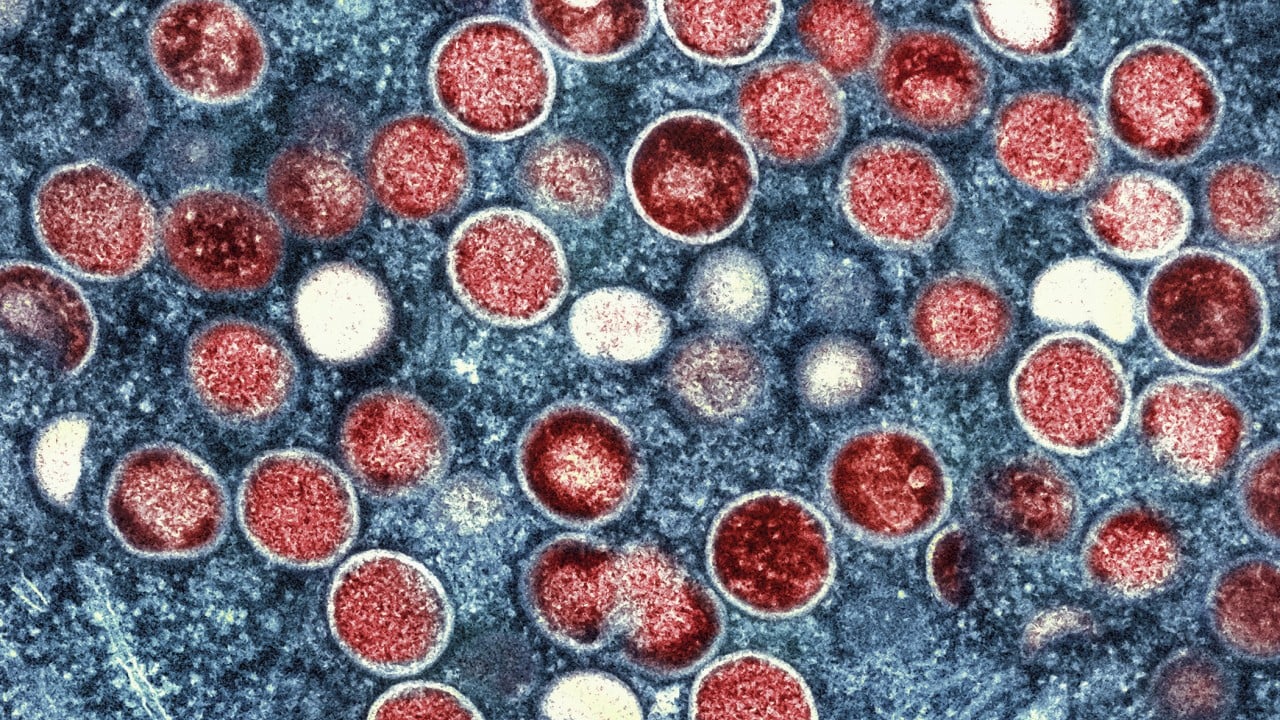
The Centers for Disease Control and Prevention just dropped another hundred million dollars into state coffers for measles response.
Blink and you will miss the real story. For another view, consider: this related article.
Washington loves a cash infusion because writing a check looks like action. It feels heavy. It sounds decisive. But dropping nine-figure grants onto state health departments while ignoring the structural collapse of public trust is like pouring water on an electrical fire. You are throwing liquidity at a credibility crisis.
I have spent years watching institutional agencies attempt to buy their way out of public relations disasters with bureaucratic funding streams. It never works. Throwing cash at a symptom while ignoring the disease of apathy is professional malpractice. State health agencies do not need another line item for outreach brochures no one reads or automated text alerts that get swiped away in notification trays. They need an entire operational rethink. Related reporting on the subject has been shared by Everyday Health.
Let us look at the lazy consensus dominating the current discourse. The narrative goes like this: measles cases are climbing due to localized pockets of vaccine hesitancy, and the only antidote is more marketing budget, more localized mobile clinics, and more stern warnings from officials in suits.
That diagnosis is fundamentally lazy.
Vaccine hesitancy is not a mysterious pathogen that arrived overnight. It is a rational symptom of irrational institutional communication. For decades, public health bureaucrats have treated the public like children who need to be managed rather than stakeholders who deserve transparency. When you sanitize data, overstate certain risks while dismissing legitimate inquiries, and weaponize compliance over comprehension, people stop listening. A hundred million dollars in federal aid will not buy back the equity that institutions burned down during the pandemic.
Let us define terms properly. Herd immunity against measles requires roughly ninety-five percent population coverage because the virus is uniquely, terrifyingly contagious. A single infected person can infect up to eighteen others in a susceptible room. It has an $R_0$ value that makes most respiratory illnesses look pedestrian. But knowing the math does not mean you understand the sociology.
State health departments receiving this new federal windfall are planning to scale up contact tracing and community engagement programs. Imagine a scenario where a county health worker knocks on a door in a suburban neighborhood with a laminated pamphlet explaining herd immunity. How do you think that interaction ends? It ends with polite dismissal at best, and hostile door-slamming at worst. Why? Because the messenger has zero relational equity with the recipient.
You cannot fix a community trust deficit with a government grant code.
What the federal strategy misses—completely and catastrophically—is the decentralization of modern information loops. People do not get their health cues from the CDC website. They get them from peer-to-peer networks, localized micro-influencers, neighborhood group chats, and fragmented social algorithms that reward emotional resonance over epidemiological consensus. Pumping money into traditional state apparatuses is like trying to capture wild horses with a bureaucratic lasso. The world has moved past centralized bulletins, yet our public health infrastructure is still behaving like it is 1995.
Let us address the elephant in the room: the downside of this contrarian stance. Am I saying that money has no utility in stopping an outbreak? No. Outbreak containment requires boots on the ground, clinical staff, laboratory sequencing, and rapid response units. If a school district in Ohio or a county in Florida faces an active cluster, those nurses and epidemiologists need resources immediately. Starving local clinics of operational funds is dangerous.
The critique is not against funding clinical response. The critique is against pretending that funding a broken communication pipeline will solve a behavioral crisis.
When states receive these federal grants, the path of least resistance is administrative bloat. Hiring more middle managers to coordinate regional committees does not put a single needle in an arm. It creates internal bureaucracy that eats up forty percent of the allocation before the first public service announcement is filmed. We have seen this playbook before. Millions vanish into consulting fees, redundant software licenses, and half-baked campaigns that accomplish nothing beyond checking a compliance box for Washington.
If we want to actually stop measles outbreaks before they breach community defenses, we have to flip the script entirely.
First, stop centralizing the message. Local health departments must empower trusted community insiders—pediatricians, nurse practitioners, local athletic coaches, faith leaders—to hold the microphone. People trust individuals who share their grocery store aisles, not bureaucrats sitting in Atlanta or state capitals. If a pediatrician with thirty years in a specific neighborhood says a vaccine is safe and necessary, it carries ten thousand times the weight of a faceless federal press release.
Second, stop dodging legitimate questions. The institutional reflex to label every inquiry as misinformation has backfired spectacularly. When parents ask nuanced questions about schedules, adjuvants, or rare adverse events, they deserve rigorous, unvarnished answers. Treat the public like adults. Acknowledge real risks openly instead of resorting to paternalistic blanket statements. Candor builds durability; spin breeds suspicion.
Third, tie every single dollar of federal support to measurable clinical outcomes, not administrative output. Stop rewarding states for producing reports or holding symposiums. Reward them when vaccination rates stabilize or climb in high-risk zip codes. If a state agency cannot demonstrate direct community-level conversion from its outreach spending, claw the money back.
The C.D.C. offering one hundred million dollars is a headline designed to soothe nervous lawmakers, not an operational masterstroke. Until we dismantle the archaic top-down command structure of public health and rebuild it around radical transparency and hyper-localized trust, we will keep fighting nineteenth-century diseases with twentieth-century budgets while wondering why twenty-first-century populations refuse to follow orders.
Stop funding the bureaucracy. Fix the conversation.